A 60 y.o. woman is undergoing a lymph node biopsy for nightsweats and a positive TSPOT
Her bp spikes to 220/110 during the biopsy and she develops chest pain, EKG changes and a trop of 2,020.
What could be wrong?
Hint: she had a pheo resected from the R adrenal in 2014.
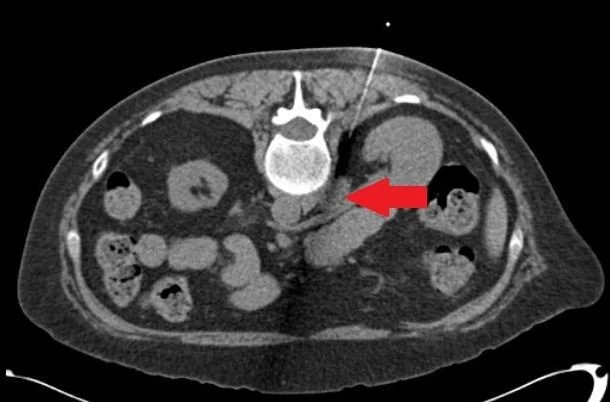
Our patient had a metastatic pheochromocytoma which triggered a hypertensive crisis and demand ischemia causing an elevated troponin. Pheochromocytomas have a lot in common with paragangliomas and behave in similar ways so they must be considered if you are considering a pheo.
Pheochromocytomas are rare neuroendocrine tumors that arise from the chromaffin cells of the adrenal glands. Paragangliomas are the extra-adrenal counterparts of pheos and arise from the sympathetic and parasympathetic chains. 0 .1% of all people with hypertension will have one of these tumors. The three P,s pain (HA), palpitations and perspiration(diaphoresis) should suggest an evaluation for pheo or paraganglioma.
Several conditions are known to be associated with pheos: von Hipple Lindau, MEN2, and neurofibromatosis
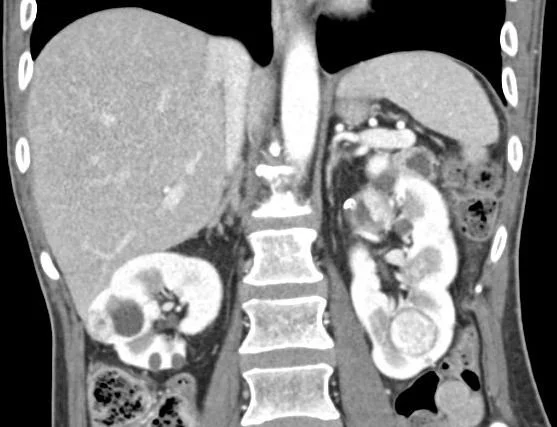
this is a patient seen in the ED recently with von Hipple Lindau and renal carcinomas
Von Hippel-Lindau is a condition in which the VHL protein is mutated and created a predisposition to multiple tumor types: central nervous system hemangioblastomas, clear cell renal cell carcinomas and islet cell tumors of the pancreas.
Multiple Endocrine Neoplasia type 2(MEN2) patients have an abnormality of the RET protein. These patients are usually diagnosed with medullary thyroid cancer and those with MEN 2A have a 95% chance of developing medullary thyroid cancer, a 50% chance of a pheo and 15-30% chance of hyperthyroidism. Neurofibromatosis type1 is associated with pheos, but the risk is much lower than with von Hippel-Linaunndau or MEN.
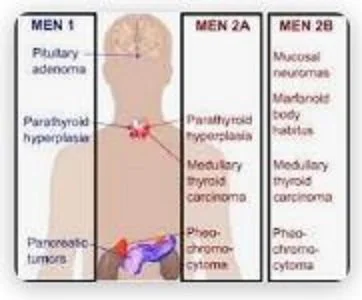
MEN syndromes can be associated with pheo or paraganglioma
Neurofibromatosis is associated with pheochromocytoma with a prevalence of 2-9%. The prevalence of NF1 is 1:3,000 and half the cases are de novo mutations. An individual must exhibit at least two of the following features to be diagnosed with NF1.
-six of mare care-au-lait spots
-2 or more neurofibromas
-freckling in the axillae or inguinal areas
-optic glioma
-2 or more lisch nodules( these are projections from the iris)
-bony thickening of a long bone cortex
-a first degree relative with NF1
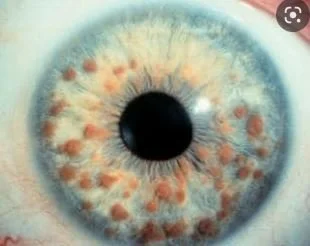
lisch spots occur in neurofibromatosis.
Martucci V, Pacak K. Pheochromocytoma and paraganglioma: diagnosis , genetics, management and treatment. Curr Prob Cancer 20114Jan-Feb:38(1):7-41.
Feingold K, Anawalt B, Boyce A, et al. endotext (internet) South Dartmouth (MA) MDText.com, Inc.;2000https://www.ncbi.nlm.nih.gov/books/NBK481899/
Lew J, Jacome F, Solorzano C. Neurofibromatosis-associated pheochromocytoma . JACS March 2008 , Vool 202(3) : 550-551.
Gruber L, Erickson D, Babovic-Vuksanovic D, Thompaon G, et al. Pheochromocytoma and paraganglioma in patients with neurofibromatosis type 1. Cliniccal Endocrinology July 2016. https://doi.org/10.111/cen.13163.
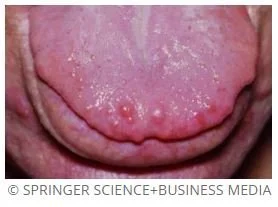
neurofibromas can occur first on the tongue